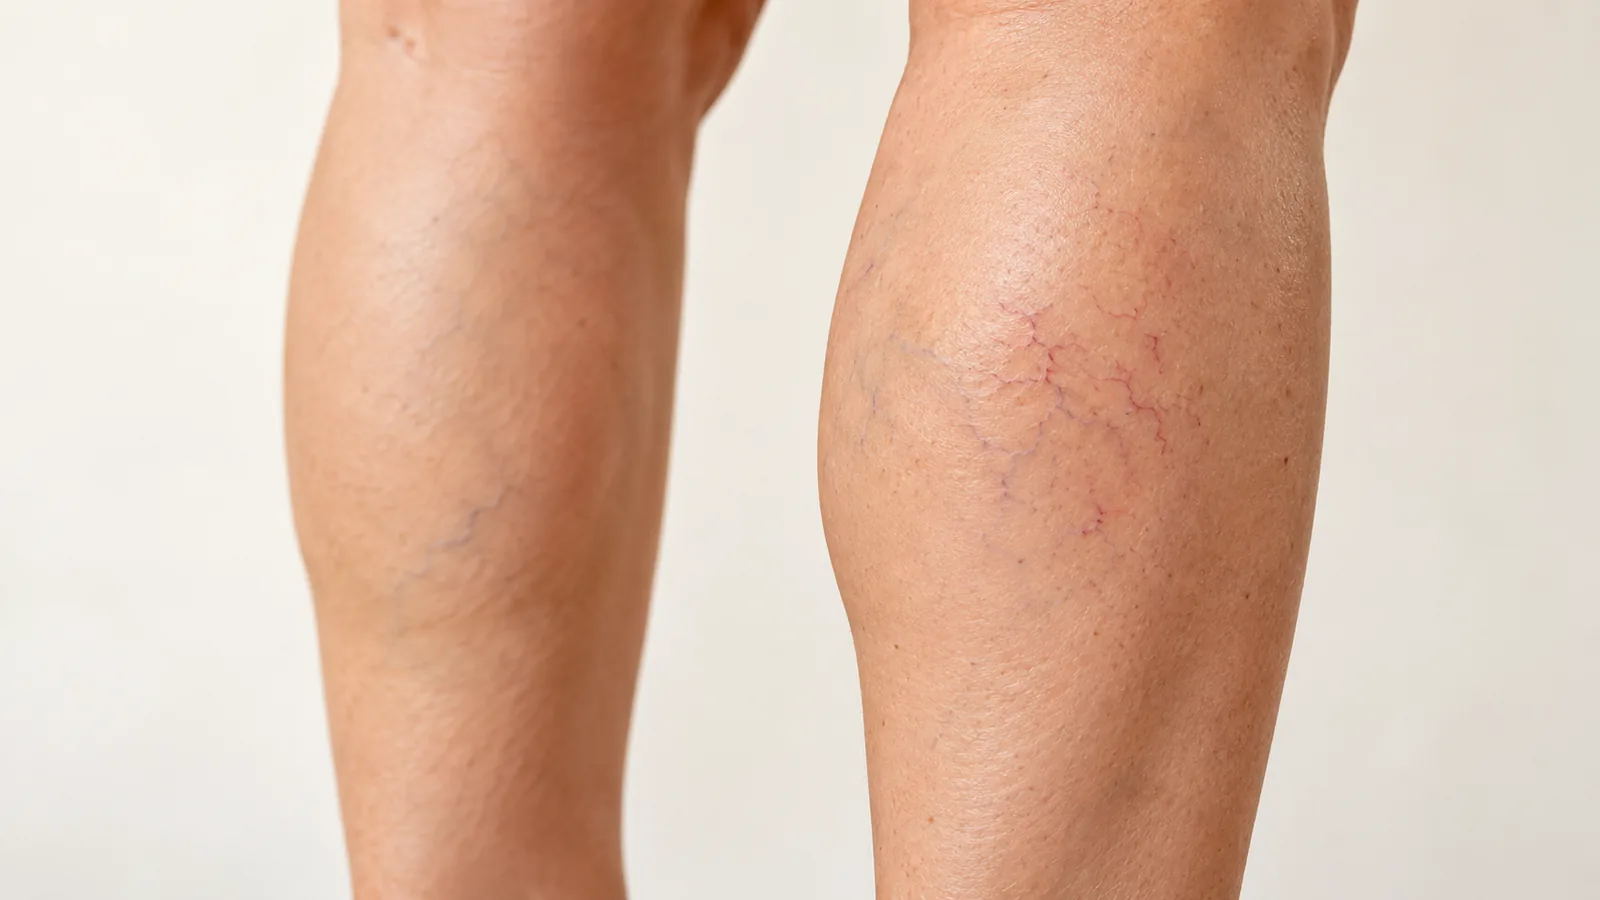
Searching for non-surgical varicose vein treatment often means looking for an option that disrupts everyday life less. However, “non-surgical” does not mean “no procedure”, “no risk” or “suitable for every vein”. Choosing an option starts with identifying the relevant segment and the goal of treatment. The information on non-surgical varicose vein care at Medivás places vascular assessment before a particular technique.
Alternatives can avoid open surgery in selected cases, but comparison requires specific information. The vein's size, course, relationship to nearby structures and the person's history may change the recommendation. This guide organises the questions worth answering before accepting treatment, particularly when different offers seem to promise similar outcomes under different technical or commercial names.
What treating a vein from inside means
Endovenous procedures act within a selected vein. Some use thermal energy and others use different mechanisms. The aim is to close a segment contributing to the problem so that blood uses other appropriate pathways. Before proceeding, the indication and the remaining circulation must make that plan reasonable for the individual patient.
A vein is not chosen simply because it is visible. The venous map and symptoms help identify the structure that may benefit from treatment. Closing a main superficial trunk does not always resolve every surface branch immediately. Additional treatment may be planned, or a review may be used to observe the response before deciding. This possibility should be explained at the outset rather than arrive as an unexpected part of the process later.
Endovenous laser and radiofrequency
Both methods use heat to act on the vein wall, although their devices and technical details differ. They are performed with ultrasound guidance and appropriate anaesthetic preparation. The vein's proximity to skin or nerves, its route and other factors can influence whether a thermal approach is suitable.
A familiar technology is not automatically the best choice for every case. Ask why it is being proposed for your anatomy, how discomfort is managed and what follow-up is needed. The decision should not rely solely on another person's account of returning to work the next day: their job, treatment extent and medical history may be quite different. A useful explanation connects the method to the findings and acknowledges any limitations.
Sclerotherapy: treating selected vessels
Sclerotherapy uses a sclerosing substance in particular veins. It can be used in several contexts, with the formulation and application adapted to the indication. Ultrasound helps where vessels need to be located or monitored beyond what can be seen at the skin surface. Medivás pressure sclerotherapy should be explained in relation to an individual plan and its associated care requirements.
Some outpatient techniques can avoid extensive incisions, but that does not remove the need for careful selection and follow-up. Understand which local changes may occur, how they are managed and which symptoms require contact. Assuming that a small injection always represents a minor medical decision can lead to important safety considerations being underestimated. Ask what the treatment is intended to achieve in the particular vessels identified during your assessment.
When surgery still has a role
Surgery remains part of the range of options despite the availability of endovenous procedures. It may be appropriate in selected circumstances or when other methods are unsuitable. Describing it automatically as a failure of modern techniques oversimplifies clinical decision-making. The useful question is which option offers a reasonable balance of benefit, risk and recovery burden in the individual situation.
Clarify whether the proposal concerns a main superficial trunk, removal of surface branches or a combination. Different procedures can be grouped under a broad label. Understanding the anatomical goal prevents comparisons between recommendations that actually address different problems. A second opinion can be helpful when explanations remain unclear or recommendations differ substantially, especially if the reasons for that difference have not been discussed.
How to compare two treatment proposals
Write down the diagnosis, the veins to be treated, the method and the intended outcome. Then compare anaesthesia, visits, aftercare, reviews and possible additional treatment. Ask which symptoms are expected to improve and which might have another cause. A more extensive proposal is not automatically better, and a very rapid advertised recovery does not replace a safety assessment.
The quotation should correspond to that plan. Check whether investigations, materials, compression when appropriate and follow-up visits are included. There is no need to decide during the first conversation if important questions remain unanswered. An elective procedure allows time to understand alternatives, organise practical support and decide whether the expected benefit justifies intervention now. Taking that time is compatible with making a confident, well-informed decision.
Understanding what happens inside the veins
Blood reaches the legs through the arteries and returns towards the heart through superficial and deep veins. Contractions of the calf muscles help move it upwards, while small valves encourage flow in the right direction. When some valves no longer close effectively, blood can flow backwards through a particular segment. This is called venous reflux and can contribute to increased pressure within parts of the venous network.
The vein visible at the surface does not necessarily explain the whole problem. It may be a branch connected to another vein with reflux, or a small surface change without significant disease in the main superficial trunks. Counting visible veins or looking at a photograph therefore cannot establish the right treatment. An examination connects the appearance with symptoms, distribution and, where appropriate, ultrasound findings.
It is also useful to separate cosmetic concerns from functional effects. Someone may be troubled by small visible veins despite having very little discomfort. Another person may experience heaviness or swelling even though changes at the surface look relatively modest. Both deserve a clear explanation, but they do not automatically require the same investigation, priority or intervention. Symptom intensity is not a precise measurement of the risk of complications either.
Family history, pregnancy, age, previous vascular events and long periods of immobility may all contribute to the overall picture. They do not establish a single cause, and they do not mean that the person has done something wrong. The consultation identifies which factors matter in that individual situation and which can realistically be changed. Understanding this distinction makes it easier to see why everyday measures may ease discomfort without removing an established vein, while a procedure targets a particular part of the circulation. Neither approach should be judged only by how a leg looks in one photograph.
What a complete vascular assessment contributes
An assessment begins with how the problem started, what changes the symptoms and how it affects everyday life. Useful details include whether one leg or both are affected, whether discomfort builds towards the evening, whether walking helps and whether anything has changed recently. Previous blood clots, procedures, pregnancies, medicines and other health conditions are also relevant to circulation and to the safety of possible treatment.
The examination may include visible veins, swelling, skin colour, temperature and skin condition. The clinician may check pulses when this helps assess arterial circulation. Leg discomfort is not always caused by veins: muscle, joint, nerve and lymphatic problems can produce overlapping symptoms. Several causes may exist together, in which case a particularly clear discussion about expectations is important before choosing an intervention.
Duplex ultrasound combines images of the structures with information about blood flow. When indicated, it can assess whether veins are open, the direction of flow and possible sites of reflux. Its purpose is not simply to add a routine test. It should answer questions that could change the diagnosis or the choice of treatment. The findings must be interpreted alongside the history and examination, rather than as a collection of isolated measurements.
Before making a decision, ask for an understandable explanation: which vein is involved, whether the symptoms fit that finding and what treatment is expected to achieve. It is equally reasonable to ask which symptoms might remain if they have a different cause. A sound decision includes alternatives, sometimes including observation. The appointment should end with a practical plan, a reason for each next step and clear advice about when to return. Knowing what uncertainty remains is useful information, not a sign that the consultation has failed to provide an answer.
Comparing conservative care and procedures
Conservative measures and procedures address different goals. Suitable activity, position changes, skin care and prescribed compression may help manage discomfort. They do not necessarily correct the reflux responsible for the problem or remove an established varicose vein. Where intervention is appropriate, the choice depends on anatomy, symptoms, medical history and the person's informed preferences, rather than on a procedure name alone.
Options used for venous disease include thermal endovenous techniques, sclerotherapy and selected surgical approaches. No single method suits every vein. Its location, course, size, relationship to skin and nerves, and the condition of the deep circulation can all change the recommendation. The fact that a technique is available at a clinic does not mean that every patient attending that clinic should receive it.
Useful comparisons cover the main objective, anaesthesia, expected number of visits, likely discomfort, temporary restrictions and follow-up. When a price is provided after assessment, it should explain what is included: investigations, the procedure, materials, reviews and any potential additional treatment. A quotation does not replace a clinical indication, and it should not be interpreted as a promise of a complete or permanent result.
Possible unwanted effects should also be discussed. Depending on the procedure, these may include bruising, inflammation, pigmentation, local discomfort or altered sensation. Less common complications can require medical attention. The clinician should explain the risks relevant to the specific technique and individual circumstances rather than provide an identical list for every treatment. Asking about alternatives, including not intervening, helps put the expected benefit in perspective. Informed consent is an individual conversation as well as a document. Having time to understand the explanation and ask questions is part of that process, even when the proposed treatment is performed as an outpatient procedure.
Building a routine you can maintain
Small, repeatable changes are often more useful than an ambitious routine that cannot fit everyday life. Alternating sitting with movement, walking within personal ability and avoiding long uninterrupted periods of stillness can help leg comfort. Where mobility is limited, the plan should accommodate that limitation instead of imposing a universal step count or a fixed exercise target on everyone.
Ankle movement and calf muscle activity contribute to the muscle pump that supports venous return. Brief movement breaks can be incorporated into a working day when appropriate for the person's clinical situation. Every break does not need to become an intense workout. Gradual, tolerable activity is usually easier to sustain than occasional strenuous efforts followed by prolonged inactivity, and the routine should remain practical when work or family responsibilities change.
When compression is prescribed, the indication and fit matter. Greater pressure does not automatically mean greater benefit. Size, skin condition, the ability to put the garment on and possible arterial disease all need consideration. A garment causing substantial pain, marked colour change or skin injury should not simply be endured without advice. Copying a relative's prescription or extending a post-procedure regimen independently is not a reliable way to choose suitable compression.
Daily care also means noticing the condition of the skin and paying attention to new changes. Rest and comfortable leg elevation may ease some symptoms, but they do not replace assessment when swelling persists or increases. These measures support a clinical plan. They do not guarantee that new varicose veins will never develop, and they do not mean that every symptom should be managed through lifestyle changes alone. A useful routine is one that supports function, can be maintained and has clear limits about when further professional advice is needed.
Warning signs that change the urgency
Not every leg problem should wait for a routine appointment. New swelling that is clearly greater in one leg, especially with pain, warmth or a change in colour, needs prompt medical assessment. Having known varicose veins does not make it safe to attribute every new symptom to them. A photograph or a messaging conversation cannot rule out a deep vein thrombosis either.
Breathlessness, chest pain, fainting or coughing up blood require urgent medical help. In Spain, the emergency number is 112. Trying to manage these symptoms by walking, massaging the leg or taking someone else's medication is not appropriate. An acute problem needs assessment on its own merits, even when a person already has a familiar explanation for occasional leg discomfort.
Bleeding from a varicose vein also calls for action. Lie down, raise the leg if possible and apply firm direct pressure with clean material over the bleeding point. Urgent help is needed if bleeding does not stop, is substantial or the person feels unwell. Even if it settles, the cause should be reviewed to reduce the risk of another episode. A homemade tourniquet should not be used.
Other changes can justify urgent or priority assessment: a wound that is not healing, a red and hot area accompanied by fever or increasing pain, or a foot that suddenly becomes cold, pale and painful. These examples explain the limits of general information; they are not a checklist for making a diagnosis at home. If the seriousness is uncertain, contact a healthcare service able to advise on urgency. A clinic's ordinary appointment channel is not a substitute for emergency services, and waiting for a reply to a non-urgent form is not appropriate when potentially serious symptoms are developing.
Assessing progress without promises of instant results
Follow-up should compare changes that matter to the agreed goal. If the priority was less heaviness, useful questions concern how a working day feels, whether walking is easier and whether rest is more comfortable. If appearance was also a goal, photographs taken under similar conditions may help document change. None of these observations replaces examination when new symptoms develop or the pattern changes unexpectedly.
Some changes after a procedure cannot be interpreted reliably in the first few days. Swelling, bruising or areas of firmness may temporarily affect appearance. The treating team should explain the expected course for the actual technique used and which findings warrant contact before the planned review. It is unwise to assume that everything is normal because treatment was minimally invasive, just as a small bruise does not by itself demonstrate treatment failure.
Reviews may involve a clinical assessment and, where indicated, repeat ultrasound. Their timing should not be copied from someone else's experience because the procedure, medical history and findings all matter. Keeping the initial report, details of the technique and written instructions supports continuity of care. If another centre is consulted later, those documents can reduce incomplete interpretation and unnecessary duplication of investigations.
Venous disease can change over time. Treating one vein does not remove the underlying tendency to develop other abnormalities, and a newly visible vein does not automatically show that previous care was performed incorrectly. The useful question is what has changed and whether there is a current reason to act. Reasonable follow-up combines realistic expectations, access to review when needed and respect for observation when an intervention is not clinically necessary. Progress is best judged over an appropriate period and against a clear baseline, rather than against an advertisement or another person's photograph.
Frequently asked questions about avoiding open surgery
### Can every varicose vein be treated with one technique? No. Anatomical and clinical differences mean a method suitable for one person may not suit another. Different types of vessel can also coexist. Personalisation is meaningful when the clinician explains which finding changes the recommendation, rather than simply using the word in a description of the service.
Does closing a vein make circulation worse?
With an appropriate indication, treatment targets a vein contributing to the problem and takes the wider circulation into account. This does not mean that any vein can be closed without assessment. Reviewing the deep veins and relevant connections helps establish whether the proposed intervention is appropriate and proportionate.
When can I drive or return to work?
This depends on the procedure, anaesthesia, symptoms and the demands of the activity. Obtain specific instructions. Do not drive with sedation, impaired function or advice to avoid it. Planning transport home may be part of preparation even when the procedure does not involve an overnight stay.
How can I arrange an assessment in Madrid?
You can request an appointment at Medivás, describe your symptoms and bring previous reports. Vascular ultrasound, when needed, helps support the decision. A useful initial outcome is understanding the indication, even if the eventual plan is observation or continued conservative management rather than immediate intervention.
Sources and further reading
- NHS · Varicose veins
- NICE CG168 · Varicose veins: diagnosis and management
- ESVS · Chronic venous disease guidelines
Educational content by Clínica Medivás. It does not provide an individual diagnosis or replace a consultation.
This content is for information only and does not replace an individual medical assessment. Seek appropriate medical care for acute or worrying symptoms.